
Educational information · Not medical advice
In brief
Tension headache vs migraine vs TMJ headache: pressing band, throbbing one-sided pain, or temple pain from your jaw — compare the patterns that separate them.
In this article
Key Takeaways
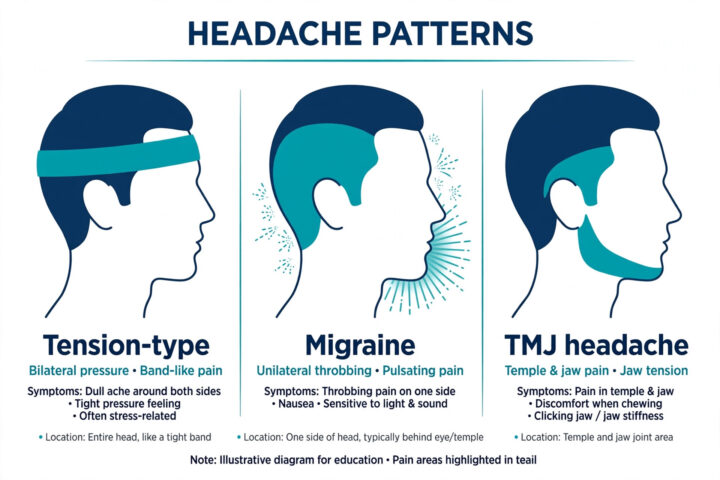
- Tension-type headache is usually bilateral, pressing or tightening, mild to moderate, and not worsened by routine activity, with no nausea.
- Migraine is often one-sided and pulsating, moderate to severe, worse with activity, and comes with nausea or sensitivity to both light and sound.
- A TMJ headache sits mainly in the temple and is changed by jaw movement, chewing, or clenching, and can be reproduced by pressing the temple muscle.
- The three overlap and can coexist in the same person, so pattern — not pain intensity alone — is what separates them.
Almost everyone who searches tension headache vs migraine vs tmj headache is asking the same question from a sore head: which one is this, and does the answer change what I should do? It does. These three headaches are treated differently, they are diagnosed differently, and one of them — the TMJ headache — will keep coming back if only the head is treated and the jaw is ignored.
The good news is that each has a recognisable pattern. The International Classification of Headache Disorders, third edition (ICHD-3, published by the International Headache Society in 2018), sets out formal criteria for tension-type headache and migraine, and a separate category for headache attributed to a temporomandibular disorder (TMD). This article walks through those patterns in plain language, puts them side by side, and explains the overlap honestly — because the overlap is real, and a checklist alone never makes this diagnosis.
What does a tension-type headache feel like?
Tension-type headache is the pressing, tightening headache most people picture as an ordinary headache. Under ICHD-3, an attack lasts from 30 minutes to 7 days and has at least two of four features: it is on both sides of the head, it feels pressing or tightening rather than pulsating, it is mild or moderate in intensity, and it is not aggravated by routine physical activity such as walking or climbing stairs.
Just as telling is what is missing. Tension-type headache has no nausea or vomiting, and at most one of light sensitivity or sound sensitivity — not both together. People often describe a band or a tight cap around the head, building gradually through a working day, especially with stress, poor sleep, or long hours at a screen. It is uncomfortable and distracting, but it rarely stops someone in their tracks the way migraine does.
One caution: “tension” in the name does not prove that muscle tension or stress caused your particular headache. It is the name of a pattern. If a bilateral pressing headache is new, changing, or happening on 15 or more days a month, it deserves the same proper assessment as any other frequent headache.
What does migraine feel like?
Migraine is a neurological disorder, not just a bad headache. ICHD-3 describes attacks lasting 4 to 72 hours when untreated, with at least two of these four features: one-sided location, pulsating quality, moderate or severe intensity, and aggravation by — or avoidance of — routine physical activity. During the attack there must also be nausea or vomiting, or sensitivity to both light and sound.
In real life that often means a throbbing pain, frequently behind one eye or in one temple, that makes ordinary movement unpleasant, drives you to a dark, quiet room, and may come with nausea. Some attacks begin with aura — temporary, fully reversible visual, sensory, or speech symptoms that build gradually. Our guide to migraine aura without headache explains that pattern in detail, including how it differs from stroke symptoms.
Migraine also tends to run in repeating attacks with a recognisable shape for that person: similar start, similar company of symptoms, similar length. A headache diary usually shows that shape clearly within a few weeks, which is one reason clinicians ask for one before changing treatment.
What is a TMJ headache?
A TMJ headache — formally, headache attributed to a temporomandibular disorder — is a secondary headache: the pain comes from a painful problem in the jaw joint, the chewing muscles, or nearby structures. ICHD-3 notes it is usually most prominent in the temple, the area in front of the ear, and/or the jaw (masseter) muscle, on one or both sides.
The evidence of causation is what separates it from a headache that merely happens in someone who also has jaw pain. At least two links should be present: the headache developed around the same time as the jaw disorder, it is aggravated by jaw motion, jaw function such as chewing, or jaw parafunction such as clenching and grinding, or it is provoked on examination by pressing the temple (temporalis) muscle or moving the jaw. The Diagnostic Criteria for TMD (DC/TMD) use the same idea in clinic: a temple headache that changes with jaw movement, function, or parafunction, and that can be reproduced as your familiar headache by palpating the temporalis or moving the jaw.
Practical clues follow from that definition. A TMJ headache is often worse after a long chew, a dental appointment, a stressful day of clenching, or a night of grinding. It may travel with jaw clicking, stiffness on waking, pain in front of the ear, or tender chewing muscles. Stress can feed it indirectly: as our article on anxiety, jaw clenching, and the stress–pain loop explains, daytime clenching is a habit many people do not notice until someone points it out.
How do the three compare side by side?
The table below summarises the ICHD-3 patterns behind the tension headache vs migraine vs tmj headache comparison. Read it as a guide to what to notice and report — not as a self-diagnosis test, because individual attacks often borrow features from more than one row.
| Feature | Tension-type headache | Migraine | TMJ headache |
|---|---|---|---|
| Where it hurts | Both sides, band-like around the head | Often one side, temple or behind the eye | Temple, in front of the ear, and/or jaw muscle |
| How it feels | Pressing or tightening, not pulsating | Pulsating or throbbing | Aching, often with jaw tenderness |
| Intensity | Mild to moderate | Moderate to severe | Varies; follows the jaw problem |
| Typical duration | 30 minutes to 7 days | 4 to 72 hours untreated | Tracks jaw use, clenching, or a flare |
| Routine activity | Does not make it worse | Makes it worse, or is avoided | Chewing and jaw movement make it worse |
| Comes with | No nausea; at most one of light or sound sensitivity | Nausea/vomiting, or both light and sound sensitivity; sometimes aura | Jaw clicking, stiffness, tender chewing muscles, morning clenching |
| A useful test clue | Pattern fits, jaw exam unremarkable | Repeated attacks with the same shape | Pressing the temple muscle or moving the jaw reproduces the familiar headache |
Location alone is the weakest clue in the table. Migraine can be bilateral, tension-type headache can feel one-sided on a given day, and a TMJ headache is often felt exactly where migraine hurts — the temple. The stronger clues are the company the pain keeps: nausea and combined light-and-sound sensitivity point toward migraine, while a headache that reliably follows chewing, clenching, or jaw examination points toward the jaw.
Can you have more than one at the same time?
Yes, and this is where honest uncertainty matters. ICHD-3 itself notes the overlap between headache attributed to TMD arising from muscle tension and tension-type headache, and advises that when the TMD diagnosis is uncertain, the headache should be coded as tension-type headache. Migraine and TMD also commonly travel together in the same person, and a person can have migraine attacks on some days and a jaw-driven temple ache on others.
That overlap has a practical consequence for treatment days. If every headache — migraine, tension-type, and jaw-driven alike — is treated with acute pain medicine, treatment days add up quickly. Used on too many days a month for more than three months, those medicines can themselves drive a near-daily headache, the pattern covered in our article on medication-overuse headache, when pain relief makes headaches worse. Sorting out which headache is which is not academic; it is how you avoid medicating a jaw problem.
When is a headache a red flag?
None of the three patterns above explains every headache, and some headaches need urgent care rather than a comparison table. Seek emergency or prompt medical assessment for a sudden headache that reaches maximum intensity within about a minute (a thunderclap headache), a first headache or a clearly changed pattern after age 50, a headache with fever, weakness, vision loss, confusion, or speech difficulty, a headache that is progressively worsening over days to weeks, or one that is worse lying down, coughing, or straining, or that wakes you from sleep. Clinicians group these warning signs under mnemonics such as SNNOOP10; you do not need to memorise the list — you need to recognise that a headache which is sudden, different, or accompanied by something else is the one to take seriously.
What should you track before your appointment?
A two-to-four-week diary makes the tension headache vs migraine vs tmj headache question far easier for a clinician to answer. For each headache, note when it started and how long it lasted, where it hurt and how it felt (pressing, throbbing, aching), what came with it (nausea, light or sound sensitivity, jaw clicking or stiffness), what you were doing beforehand (chewing, clenching, a poor night’s sleep, a skipped meal), and any medicine you took and on how many days that month.
Bring that diary to whichever appointment you book first — a doctor for the headache pattern, or a dentist or orofacial pain specialist when jaw signs are prominent. If both patterns appear, say so plainly. The diary, plus a jaw examination that tries to reproduce your familiar headache, usually does more to separate these three than any single scan in a person without red flags.
Frequently asked questions
How can I tell a tension headache from a migraine?
Compare the pattern, not just the pain level. Tension-type headache is usually on both sides, pressing or tightening, mild to moderate, not worsened by routine activity, and without nausea, with at most one of light or sound sensitivity. Migraine is often one-sided and pulsating, moderate to severe, worse with activity, and brings nausea or sensitivity to both light and sound.
Can TMJ really cause a headache in the temple?
Yes. Headache attributed to a temporomandibular disorder is usually most prominent in the temple, in front of the ear, and in the jaw muscle. The key evidence is a link to the jaw: the headache is aggravated by chewing, jaw movement, or clenching, or it can be reproduced by pressing the temple muscle or moving the jaw during an examination.
Can you have migraine and a TMJ headache at the same time?
Yes. Migraine, tension-type headache, and TMJ headache overlap and can coexist in the same person, sometimes on different days and sometimes blended into one bad day. That is one reason a headache diary matters: it shows whether there are two patterns with different triggers and company, which changes how each should be managed.
When should I see a doctor instead of comparing symptoms at home?
Seek urgent care for a sudden thunderclap headache, weakness, vision loss, speech difficulty, confusion, fever, a headache that is rapidly worsening, or any headache that is clearly different from your usual pattern. Book a prompt appointment for a first headache after age 50, headaches on 15 or more days a month, or any frequent headache you cannot confidently place.
Conclusion
The tension headache vs migraine vs tmj headache question is answered by pattern. Pressing, bilateral, and quiet company suggest tension-type headache. Pulsating, one-sided, activity-averse, and accompanied by nausea or light-and-sound sensitivity suggests migraine. A temple headache that follows the jaw — chewing, clenching, and examination — suggests a TMJ headache. Many people honestly have more than one, which is exactly why the diary and the jaw examination matter.
If your headaches are frequent, changing, or tangled up with jaw pain, take the pattern you have tracked to a clinician rather than settling the label alone. Getting the label right is what gets the right problem treated.
This article is for educational purposes only and is not medical advice. It does not diagnose any condition or recommend a specific treatment for you. Seek emergency care for a sudden severe headache, weakness, vision loss, speech difficulty, or a headache unlike anything you have had before, and discuss recurrent headaches with your own clinician or dentist.
Sources
- International Headache Society — The International Classification of Headache Disorders, 3rd edition (ICHD-3), 2018: criteria for tension-type headache (section 2), migraine (section 1), and headache attributed to temporomandibular disorder (section 11.7), as summarised in the peer-reviewed review at PMC — Debate: differences and similarities between tension-type headache and migraine.
- Schiffman E, et al. Diagnostic Criteria for Temporomandibular Disorders (DC/TMD) — headache attributed to TMD criteria: temple headache modified by jaw movement, function, or parafunction, reproduced by temporalis palpation or jaw movement; sensitivity 0.89, specificity 0.87, at PMC — DC/TMD and ICHD-3 headache table.
About this information
Consult the sources listed in the article. This notice does not certify an individual clinical review.
This article is for education only and is not medical advice. Talk to a qualified clinician about your own symptoms.


0 Comments